Category: Uncategorized

  • Woodlands in urban areas linked to reduced antidepressant use

    Improving and maintaining woodlands in deprived communities is linked with reduced antidepressant and anti-anxiety medication use, new joint research from the OPENspace research centre and CRESH suggests.

    People living in deprived communities are less likely to use medication for depression and anxiety if they have easy access to well-maintained woodlands, the study found.

    Researchers at the Universities of Edinburgh and Glasgow analysed data from more than 129,000 people over five years.

    The study is one of the largest analyses of its kind, assessing how investments in local woodlands in and around towns in Scotland affect people’s mental health.

    The researchers used NHS prescription records and census data to see whether people living within a 10-minute walk of an improved woodland area were more or less likely to be taking medication for depression or anxiety.

    Woodland improvements had been supported through Scottish Forestry’s Woods In and Around Towns (WIAT) initiative, which provided funding for practical improvements such as new footpaths, better signage, and community events.

    The initiative prioritised areas that were more socially and financially disadvantaged, where woodlands required improved management to reduce barriers and enable more local people to use and enjoy them.

    People living in urban deprived communities that were close to a woodland area that had been made more welcoming and easier for people to use were 10 per cent less likely to be prescribed antidepressants and six per cent less like to be prescribed anti-anxiety medication, than those living further away.

    This was the case even when accounting for other factors linked to mental health outcomes, such as demographics and poverty.

    The benefit of living near these woodlands showed up for the same people even when their proximity to these woodlands changed. For example, when someone moved closer to an improved woodland, their need for medication went down.

    By tracking the same individuals over time, the researchers say they can be more confident that it was the woodland improvements making the difference, rather than simply healthier or wealthier people happening to live in greener areas.

    Professor Catharine Ward Thompson of the OPENspace Research Centre at the University of Edinburgh’s College of Art, who led the study, said “The research provides stronger evidence on the mental health benefits of woodland improvements for local communities than was possible in earlier studies. It also shows that these benefits may contribute to reducing inequalities in health across the population.”

    Dr Scott Ogletree, of the OPENspace Research Centre at the University of Edinburgh’s College of Art, who undertook the analysis, said: “For the first time, we have an opportunity to link data on mental health services with a long-term national urban forestry intervention programme to offer the kind of evidence required to inform future forestry policy.

    Our results tell us that relatively modest investments in local greenspaces can make a real difference to people’s mental health. Nature focused initiatives like WIAT can be a valuable tool to complement ongoing efforts to improve wellbeing and mental health.”

    Around one in eight people globally live with a mental health condition, and those in poorer communities tend to be hit hardest. At the same time, these are often the communities with the least access to good quality parks, woodlands, and greenspaces.

    The researchers say that their findings make a case for integrating nature-based interventions into public health strategies, particularly in urban areas where greenspace can be limited and poorly maintained in certain neighbourhoods.

    The research team have worked with experts from Scottish Forestry and Forest Research for over 20 years to gather evidence on the social and health benefits that local woodlands can offer to communities, pioneering work on this topic within Europe.

    Minister for Agriculture, Marine and the Islands Jim Fairlie, said: “This groundbreaking study provides further compelling evidence of the benefits that local woodlands deliver for people and communities. The association between the investment in woods in and around Scotland’s towns and cities, and lower prescription use for depression, and anxiety highlights the importance of continuing to expand, manage and improve these valuable green spaces.

    “The Scottish Government is committed to increasing woodland creation across Scotland, with a target of 18,000 hectares per year by 2029/30. We are also committed to increase tree planting in urban areas to improve air quality, support biodiversity and enhance quality of life for communities across the country.”

    The research used census data from the Scottish Longitudinal Study which tracks the lives and health of thousands of people in Scotland to help researchers understand what affects people’s wellbeing.

    The study is published in The Lancet Planetary Health. The paper is available here: https://www.thelancet.com/journals/lanplh/article/PIIS2542-5196(26)00076-8/fulltext DOI – 10.1016/ j.lanplh.2026.101503.

    The research was supported by the Economic and Social Research Council (ESRC) and the GroundsWell Consortium, a UK-wide research partnership funded by the UK Prevention Research Partnership (UKPRP), that studies how green and blue spaces, can improve health and reduce health inequalities.
  • New research shows plausible mechanisms between sunlight exposure and metabolic health

    Created in BioRender. Stevenson, A. (2026) https://BioRender.com/ p885jgn

    Our new study published in Scientific Reports suggests that sunlight exposure supports metabolic health, using data from over 400,000 UK Biobank participants. We find that short-term (day-to-day) sunlight exposure was associated with lower blood glucose levels and long-term sunlight exposure with lower likelihood of being diagnosed with type 2 diabetes in a dose-dependent manner, after extensive adjustment.

    Why sunlight?

    Poor diet, physical inactivity, and excess weight are well-known risk factors for type 2 diabetes; however, there is growing evidence that sunlight exposure may play a role in cardiometabolic health, through several plausible mechanisms.

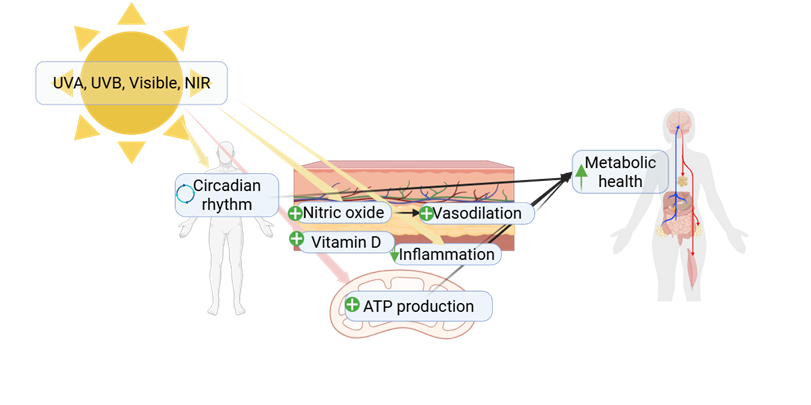
    For example, dermal ultraviolet exposure (UV) releases nitric oxide (NO) from skin stores within minutes (with levels remaining elevated for days), promoting vasodilation and suppressing inflammation. Red and near-infrared light, meanwhile, have been demonstrated to stimulate mitochondrial ATP production and suppress inflammation. Participants of a randomised trial who were exposed to 15 minutes of red light had 28% lower blood glucose levels after glucose intake compared to the placebo group.

    Sunlight and metabolic health: what we did

    We tested this using two complementary approaches in UK Biobank. First, we looked at whether people who happened to attend their health assessment on sunnier periods had lower blood glucose readings than those assessed on a less sunny period, adjusting for temperature. This was measured using satellite estimates of UVA radiation at each participant’s residential location, averaged separately over the two days up to and including the assessment and over the preceding seven days.

    We compared people assessed on the same day of the week, month and year to rule out seasonal and weekly patterns. This design rests on two independent, exogenous sources of variation: assessment scheduling and day-to-day weather variation that determines sunlight levels. For a variable to confound our estimates, it would therefore need to be associated with both the scheduling decisions made, and the specific weather conditions on the day a participant happened to be scheduled, which is unlikely. This assumption was supported by strong balance in measured participant characteristics across sunny and less sunny days.

    Second, we looked at longer-term sun exposure, using how often someone reported using a sunbed or solarium as a marker of habitual sun-seeking behaviour (non-user, occasional user, and frequency) and tracked participants from age 20 until either a diabetes diagnosis or the end of follow up, whichever came first. We adjusted for several clinical, socioeconomic and demographic variables.

    What we found

    In winter, people assessed on days with higher 2-day and 7-day average ambient sunlight exposure had modestly lower blood glucose levels. In spring, the same pattern held, but only for the 7-day average exposure.

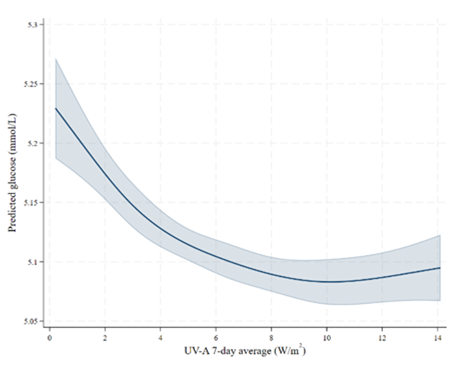
    The relationship was not linear. Predicted glucose levels dropped most steeply at low sunlight levels and then plateaued, meaning the benefit of extra sun was greatest from low baseline levels, with diminishing returns once exposure was already moderate. Because winter UVB in the UK isn’t strong enough to make vitamin D in skin, this points to sunlight acting through a route other than vitamin D.

    Associations between 7-day ambient ultraviolet A (UVA) radiation exposure and predicted glucose concentrations (mmol/L).

    Longer-term sun exposure was associated with lower type 2 diabetes diagnosis. Compared with solarium or sunbed non-users, occasional users had a 14% lower hazard of type 2 diabetes diagnosis, and frequent users a 22% lower hazard, a dose-response pattern.

    Differences in measured vitamin D were too large to be explained by solarium use alone, which was relatively modest in the cohort (an average of approximately once every two months among occasional users), consistent with solarium use tracking broader sun-seeking habits. Therefore, we regard this measure as a proxy for sun-seeking behaviour more generally.

    What do these findings mean for public health?

    The UK is a low sunlight country, where the UV index rarely exceeds 5 and winters are characterised by short, dark days. Our findings suggest that insufficient sunlight exposure may be an underrecognised but significant risk factor for impaired glucose regulation and type 2 diabetes.

    Sunlight remains a known carcinogen, and photoprotection is still important. At the same time, in low sunlight countries, moderately higher exposure could reduce the risk of type 2 diabetes, a disease responsible for substantial morbidity and premature mortality, so even a modest effect at the population level could translate into a meaningful public health benefit.

    We do not argue for solarium use as a way to reduce diabetes risk. Our solarium use variable likely reflects broader sun seeking behaviour rather than solarium exposure itself. Sources and doses of sunlight to achieve a safe, net health benefit remains to be established across different skin types.

    A sensible public health angle may be to promote active outdoor living, which could improve metabolic health through both greater physical activity and greater sunlight exposure.

    Stevenson, A.C., Weller, R.B., Lindqvist, P. et al. Sunlight exposure is associated with lower blood glucose levels and type 2 diabetes. Sci Rep (2026). https://doi.org/10.1038/s41598-026-66100-4

    This work was supported by Health Data Research UK (grant ID: EDIN1), which is funded by the UK Medical Research Council, Engineering and Physical Sciences Research Council, Economic and Social Research Council, Department of Health and Social Care (England), Chief Scientist Office of the Scottish Government Health and Social Care Directorates, Health and Social Care Research and Development Division (Welsh Government), Public Health Agency (Northern Ireland), British Heart Foundation and the Wellcome Trust. This work was supported in part by UKRI’s Securing Better Health, Ageing and Wellbeing strategic theme.

    PL was supported by Skarmans stiftelse, and the Swedish Research Council.

    ACS was also supported by a Fonds de recherche du Québec – Santé Postdoctoral Award (FRQS; https://doi.org/10.69777/353073)

  • The Uneven Rise of No/Lo Alcohol Drinks in Great Britain: A Look at Local Shops

    New work from the CRESH team has found a significant increase in the availability and sales of no and low alcohol (No/Lo) beverages in convenience stores across Great Britain. At the same time, the growth in availability and sales of these products was disproportionately higher in less deprived neighbourhoods of the country. These findings have some important implications for public health, particularly given the mixed evidence on whether No/Lo beverages act as substitutes for standard alcohol products (potentially reducing harm) or as supplements (potentially increasing overall consumption).

    The Growth of No/Lo Products: a case study in Great Britain

    No/Lo beverages are alcohol-mimicking drinks that contain no or low amounts of alcohol, and their popularity has grown rapidly across high-income countries reflecting changes in consumer preferences and drinking behaviours. Our recent CRESH study, published, with colleagues in Sheffield, in Addiction, examined how the availability and sales of No/Lo products have evolved in local stores across Great Britain between 2018 and 2022. We found that in 2018, only 34% of small retailers sold No/Lo products, rising to 68% by 2022.

    However, the availability and sales of No/Lo beverages differed across neighborhoods with varying levels of deprivation. By 2022, retailers in more affluent neighbourhoods recorded 33% higher sales of No/Lo products and offered more than twice as many products as those in the most deprived areas. Compared with 2018, we identified that these inequalities in availability and sales between the most and least deprived neighbourhoods have widened over time.

    This study draws on data from more than 11 million alcohol transactions from 1,432 retailers operating between 2018 and 2022 across Great Britain. This comprehensive dataset is particularly valuable, as such data are rarely accessible due to high costs and commercial sensitivity. Previous research has largely relied on survey data, which can be affected by recall and social desirability bias and do not capture geographic variation in availability and purchasing patterns. In addition, most existing studies have focused on sales in bars and pubs, whereas this study captures purchasing in retail settings. This is particularly relevant in a context where alcohol consumption at home is increasing, and local shops enable quick and often spontaneous purchases.

    What do these findings mean for public health?

    These findings align with previous research showing that individuals with higher socioeconomic status are more likely to consume No/Lo products, often linked to greater health awareness and lifestyle changes, particularly since COVID-19. These differences in preferences and purchasing power are likely reflected in spatial patterns of availability and sales, with higher uptake in more affluent areas. This can be also explained by the influence of large transnational alcohol companies. Product availability, range, and marketing are shaped by market forces that tend to favour more commercially attractive locations, reinforcing geographic inequalities.

    The public health implications of this uneven distribution remain uncertain. Evidence is mixed on whether No/Lo products reduce overall alcohol consumption (as substitutes) or increase it (as complements). If they do contribute to harm reduction, our findings suggest that these benefits are currently concentrated in more affluent communities—raising concerns about widening inequalities, given that alcohol-related harm is higher in more disadvantaged groups.

    This points to the need to consider equity in how No/Lo products are distributed and promoted. Potential policy responses could include incentives for retailers in more deprived areas to stock No/Lo options, alongside awareness campaigns tailored to different social groups. These approaches could complement existing measures such as alcohol taxation and minimum unit pricing (MUP), which may also make No/Lo products relatively cheaper and therefore more attractive alternatives.

    However, framing No/Lo products as a public health solution requires caution. Increased availability may contribute to the normalisation of alcohol consumption. Major alcohol companies are increasingly promoting No/Lo products, potentially using them to strengthen brand visibility. Such practices may normalise drinking behaviours and indirectly reinforce demand for higher-strength products, thereby undermining anticipated public health benefits. There are also concerns about a possible “gateway” effect, particularly among young people, who can purchase zero-alcohol products and may not clearly distinguish them from alcoholic beverages. This raises questions about the role of No/Lo products in shaping drinking norms from an early age.

    An uneven rise—and what comes next

    The study findings suggest that public health responses to the expansion of No/Lo products should adopt a geographical lens, accounting for regional contexts and inequalities. Any potential benefits or harms are unlikely to be evenly distributed under current market conditions. Further research is needed to better understand whether No/Lo products act as substitutes for or supplements to standard alcohol, particularly by examining: (i) who is being reached; (ii) which populations lack access; and (iii) how retail availability shapes consumption opportunities across different areas. Until stronger evidence is available on harm-reduction effects, consumption patterns, and potential unintended consequences, policies aimed at promoting No/Lo availability should be approached with caution.

    This is particularly relevant in a context where the UK Government has committed to delivering a significant increase in the availability of alcohol-free and low-alcohol drinks.

    Despite this, No/Lo beverages accounted for just 0.25% of total alcohol sales in local shops I 2022 in Great Britain, suggesting that their current impact—whether as substitutes or supplements—is likely to be limited. However, further investigation is warranted.

    This work was funded through the SPECTRUM consortium.

    Roberto Valiente Borox

  • Website update in progress

    Here at CRESH we are (finally) getting around to a website refresh. Please bear with us whilst we reorganise and things look a bit clunky or don’t quite work as they should…

  • Job opportunity: urban forestry and human wellbeing

    We are currently looking to recruit a postdoctoral researcher to contribute to an ESRC funded study concerned with the role of urban forestry in understanding human wellbeing, particularly amongst children.

    https://elxw.fa.em3.oraclecloud.com/hcmUI/CandidateExperience/en/sites/CX_1001/job/339

    Fixed Term, 19 months, Full Time (35 hours per week)

    1/04/2021 – 30/10/2022 (dates negotiable)

    Closing date: 12th February 2021

    The researcher will be appointed based on the statistical and geospatial skills that this study will require. They will be responsible (under supervision of the Investigator team) for preparing and quality checking variables to measure woodland and forest exposure over time. They will also be responsible for identifying relevant data from the Scottish Longitudinal Study (SLS) and associated linked health datasets to provide longitudinal data for SLS members and their children over the period of the WIAT programme, and for undertaking appropriate statistical analyses.

    The post involves working in the context of two world-leading centres of research, exploring links between environment and health. The post is based in OPENspace research centre, which focuses on inclusive access to outdoor environments and their associated benefits for wellbeing and quality of life. The study will involve close collaboration with the Centre for Research on Environment, Society and Health (CRESH), a virtual centre joining scientists from the Universities of Edinburgh and Glasgow, focused on exploring how physical and social environments can influence population health, for better and for worse.

    The successful candidate will play a lead role in utilising environmental datasets provided by Scottish Forestry (SF) to extract and process relevant geographical data that records details of SF’s Woods In and Around Towns (WIAT) programme from 2005-2015, link them to individual level census, health and child development data, and use appropriate analyses to provide better evidence on the contribution urban forestry can make to human wellbeing. The post-holder will contribute to final publications and support the impact activities relating to the research.

    The study and work of the post-holder will be overseen by Professor Catharine Ward Thompson, as Principal Investigator, with experience of multi-disciplinary research and engagement with research partners and end-users. Co-supervision of the post-holder by Co-Investigators (Co-Is) Professor Jamie Pearce and Dr Tom Clemens (CRESH, University of Edinburgh) will assist with details of data identification, manipulation and longitudinal analysis. The post-holder will also collaborate with Co-I Professor Richard Mitchell (MRC/CSO Social & Public Health Sciences Unit/CRESH, University of Glasgow) on operationalisation, linkage and analysis of environmental datasets in relation to health outcomes.

     Other key contacts will include liaison with staff in Scottish Forestry, Forest Research, Public Health Scotland and other stakeholders as necessary to undertake the project, and to share and disseminate its results.

    For further details please contact Professor Catharine Ward Thompson c.ward-thompson@ed.ac.uk

  • Job Opportunity at CRESH

    We are looking to appoint a Postdoctoral Researcher in the field of ‘Environment and Health for a period of 4 years to contribute a UK Prevention Research Partnership (UKPRP) Consortium – SPECTRUM (Shaping Public hEalth poliCies To Reduce ineqUalities and harm) https://www.ed.ac.uk/spectrum.   SPECTRUM has an ambitious programme of research, knowledge exchange and public engagement focusing on the commercial determinants of health relating to tobacco, alcohol and food.

    The successful candidate will play a lead role in a programme of work aiming to identify how the local environment can be shaped to change behaviour, prevent harm and reduce inequalities. The aim is to examine the intended and unintended impacts of (and interventions in) the local commercial environment on the consumption of unhealthy commodities. The focus of this role will be to conduct spatial and quantitative analyses, contribute to final publications and help to accelerate the impact of the research.

    For further details – including how to apply – can be found here.

  • What next for tobacco control in Scotland?

    New research from the CRESH team using data from 124,566 shopping baskets purchased in convenience stores across Scotland has found that the purchase price of tobacco is lower in more disadvantaged neighbourhoods, largely because of the higher sales of the cheapest brands in these areas.

    Cigarette smoking is one of the leading causes of preventable ill-health, hospitalisations and deaths in Scotland. Approximately 19% of adults in Scotland smoke, this rises to 32% in our most deprived fifth of neighbourhoods and falls to 9% in the most affluent neighbourhoods. As Scotland moves towards a ‘Tobacco Endgame’ the Scottish Government have a target to reduce smoking prevalence to less than 5% by 2034. A recent review of smoking projections by CRUK however suggests that Scotland may miss this target by 16 years in the poorest neighbourhoods. It is important that we continue to explore all potential determinants of smoking, particularly those that drive smoking in our most deprived communities.

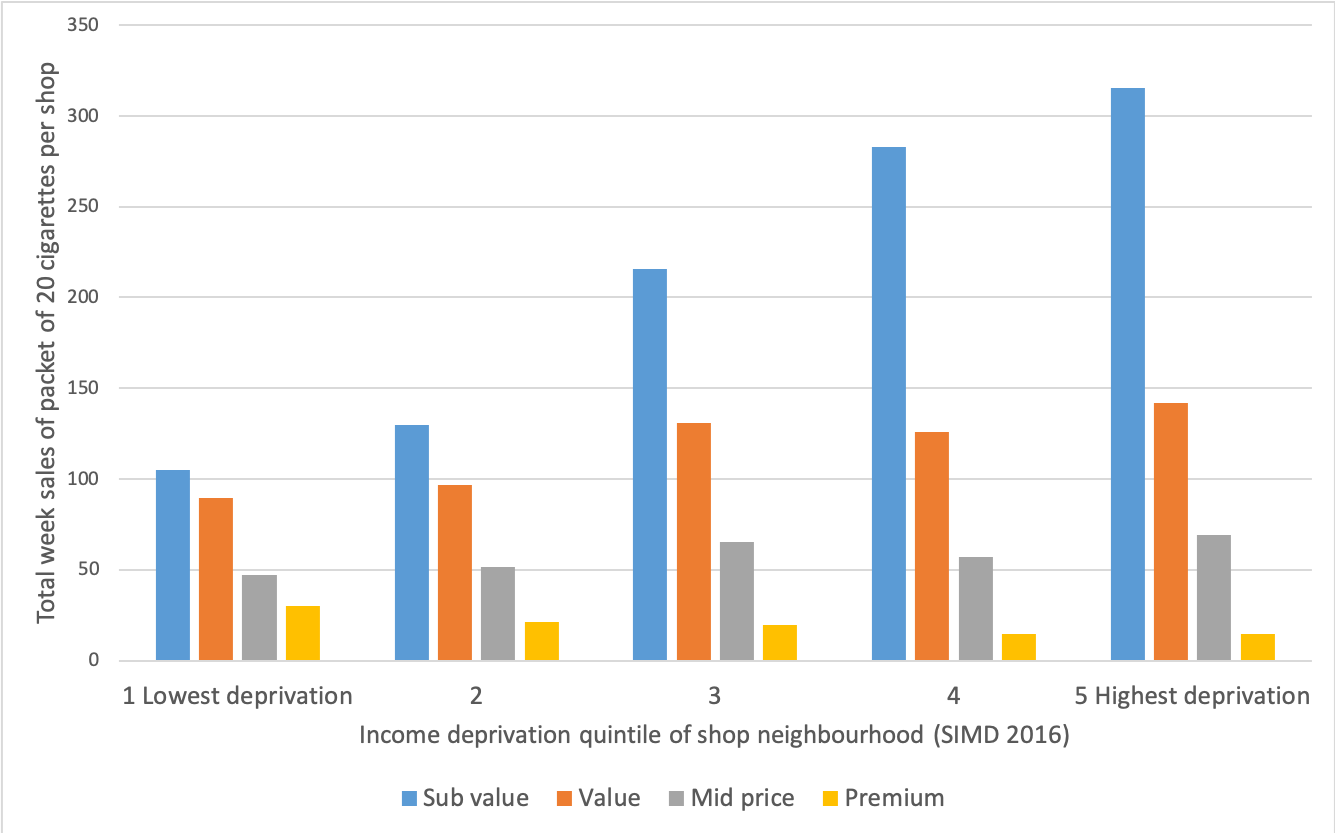
    We know that tobacco price is one of the most important determinants of smoking behaviour and that many smokers are price sensitive. Whilst it may appear that all tobacco products are becoming increasingly expensive, research suggests that the average tobacco price in the UK has remained relatively unchanged in real terms over the past 20 years in spite of numerous tax increases. A practice, known as ‘undershifting’, has seen tobacco companies limit price increases on the cheapest brands and instead increase the price of the most expensive brands by larger margins, thus absorbing the tax increases on the cheapest cigarettes allowing them to remain cheap (Hiscock et al. 2018).  As a result, the price of the lowest priced cigarette brands has remained relatively steady and the tobacco market as a whole has become increasingly stratified by price between the cheapest ‘sub value’ , ’value’, ‘mid price’ and high priced ‘premium’ brands. We wanted to understand these differentials in price a little better, so we carried out some research that was published recently in Tobacco Control. We explored whether the price paid for tobacco (both cigarettes and roll your own tobacco) was different in different types of neighbourhoods. We compared areas by deprivation, by the density of tobacco outlets and by rurality.

    We analysed tobacco purchase data provided to us by The Retail Data Partnership. We looked at more than 124,000 purchases in 274 stores across Scotland in April 2018. For cigarettes the average price paid for a pack of 20 was £8.49, ranging from £7.20 to £13.25. For roll your own tobacco (RYO) 30g the average price paid was £12.14, with prices ranging from £9.80 to £15.99. We found that the price paid for tobacco did vary by neighbourhood type. In neighbourhoods with the lowest average household income the average purchase was 50p less for a pack of 20 cigarettes, and 34p less for roll your own tobacco compared with the most affluent neighbourhoods.

    We then asked whether this was driven by individual brands being cheaper in more deprived areas, or whether cheaper, sub-value, brands were just more popular in such places. We found little evidence that individual brands were priced differently. Although the cheaper brands are the most popular in all neighbourhoods and across Scotland, accounting for 52% of sales, there’s a big difference in popularity between more and less deprived areas, In the most deprived areas these brands account for 58%  of sales, but in most affluent areas it was just 39% (See Figure 1 below). So, it is the dominance of cheaper brands in more deprived areas that drives the 50p difference in average price paid per pack between deprived and affluent areas. Remember this matters because the tobacco companies work to subdue tax-based price rises on the cheapest brands.

    We also explored whether the density of tobacco retailers and/or rurality had an impact on tobacco price. We found little evidence of a density effect, but we did find that the individual brands analysed were significantly cheaper in rural areas.

    So what does this mean and what can we take from this research? It is clear from the CRUK review that we need to work harder in order to reach the 2034 target of less than 5% of the population smoking. Price is a lever that we can pull, but to date this has been largely done through tax increases. This research shows us that the cheapest brands are the most popular in all neighbourhood types, but much more so in our most deprived neighbourhoods where smoking rates are highest. We found that the price paid for tobacco is lower in more deprived areas compared to more affluent areas. Our results confirm that the dominance of cheaper, so called ‘sub-value’ brands in more deprived areas, is a driving force behind the difference in price paid for tobacco between neighbourhoods. This highlights the importance of cheaper tobacco products to the consumer and the market.  Cheap tobacco may help tobacco companies to retain price sensitive consumers who live in the most deprived areas, which, in turn, contributes to health inequalities. In addition to increases to the duty rates on tobacco, more radical policy responses are likely to be required. These include a combination of minimum unit pricing (MUP) and a price cap at the upper end. The MUP would raise the cost of cheaper cigarettes and the price cap at the upper end would prevent the more expensive brands being used to ‘protect’ the cheaper ones from tax rises.

    With growing international interest in the ‘Tobacco Endgame’, policymakers should identify measures that counter industry tactics that enable the continued sales of cheap tobacco. We published this paper in the first week of the COVID-19 pandemic in the UK. These are clearly strange times and we should rightly focus on the public health impacts of the global pandemic, and in particular the vast health inequalities that are arising. We must not however forget that the public health challenges we were faced with before this pandemic remain. Tobacco, and other unhealthy commodities, require our attention and the inequalities that arise from them remain a matter of social justice.

    You can find the paper here:

    Shortt, N., Tunstall, H., Mitchell, R., Coombes, E., Jones, A., Reid, G. & Pearce, J. Using point-of-sale data to examine tobacco pricing across neighbourhoods in Scotland. Tobacco Control, Published Online First: 19 March 2020. doi: 10.1136/tobaccocontro

    References

    Hiscock R, Branston JR, McNeill A, et al. Tobacco industry strategies undermine government tax policy: evidence from commercial data. Tob Control 2018;27:488 LP – 497. doi:10.1136/tobaccocontrol-2017-053891

  • Two Postdoctoral Researchers (Health & Environment)

    We are currently seeking to recruit two Postdoctoral Researchers (Health & Environment) to join the CRESH team at the University of Edinburgh and contribute to two studies on the geography of unhealthy commodities.

    The first position is part of the UK Prevention Research Partnership (UKPRP) Consortium – SPECTRUM (Shaping Public hEalth poliCies To Reduce ineqUalities and harm). SPECTRUM has an ambitious programme of research, knowledge exchange and public engagement focusing on the commercial determinants of health relating to tobacco, alcohol and food.

    The second role will contribute to an ESRC funded project ‘Change in alcohol and tobacco availability, population health and the lived experience’ which will measure change in the availability of alcohol and tobacco in Scottish neighbourhoods over time and explore how this change relates to health outcomes and how residents experience the availability of alcohol and tobacco in their neighbourhoods.

    Closing date for both positions is 16th October 2019.

    Please get in touch with Professor Jamie Pearce or Professor Niamh Shortt to discuss either role: Jamie.Pearce@ed.ac.uk Niamh.Shortt@ed.ac.uk

    https://www.jobs.ac.uk/job/BVI122/postdoctoral-researcher-health-and-environment-tobacco-and-alcohol

    https://www.jobs.ac.uk/job/BVI153/postdoctoral-researcher-health-and-environment

  • New ESRC funded study on Tobacco and Alcohol

    We are delighted to announce that we have been awarded funding from the ESRC for a project exploring tobacco and alcohol environments in Scotland. The project ‘Change in alcohol and tobacco availability, population health and the lived experience’ will be funded for 3 years, beginning December 2019 for a total of £761, 470. The project will be led by Professor Niamh Shortt with co-investigators from the University of Edinburgh (Professor Jamie Pearceand Dr Tom Clemens), Glasgow Caledonian University (Professor Carol Emslie) and the MRC/CSO Social and Public Health Sciences Unit, University of Glasgow (Professor Richard Mitchell).

    This research will measure change in the availability of alcohol and tobacco in Scottish neighbourhoods over time and explore how this change relates to health outcomes and how residents experience the availability of alcohol and tobacco in their neighbourhoods. The findings will be important because smoking and alcohol consumption are leading causes of illness and death. In Scotland smoking causes one in every 5 deaths and one in 20 deaths is related to alcohol. This harm is not equally shared; those on the lowest incomes suffer the greatest harm. These illnesses and deaths are preventable. The World Health Organisation recommends that nations prioritise interventions that reduce the supply of alcohol and tobacco.

    Why might neighbourhood supply of alcohol and tobacco matter? Research suggests that when there are a lot of outlets in a neighbourhood this impacts upon consumption in three ways. 1. The outlets may be more competitive and drive prices down to attract customers. 2. Oversupply may normalise the products when they are sold alongside everyday commodities, such as bread and milk. 3. Tobacco and alcohol may simply be easier to buy in areas where there are more outlets.

    In order to explore the relationship between supply, behaviour and harm we need data on the location of every outlet in Scotland selling tobacco and/or alcohol. Ideally, to be able to say something about whether the relationship may be causal, we need this data over time. We have already collected data on the specific location of every outlet selling tobacco and licensed to sell alcohol over multiple time periods (2012 and 2016 (nationwide alcohol and tobacco – see paper here) and 2008 (alcohol in four cities – see paper here)). As part of this project we will collect updated data for 2019/20. This will allow us to measure this change over time. Using an approach called trajectory modelling we will group neighbourhoods that have had a similar degree of change; some neighbourhoods may have lost, or gained, local shops or pubs, whereas some may not have changed at all. We will then identify features of these neighbourhoods that may be driving this change, for example the age profile of the population or poverty levels. This will help policy makers understand the drivers of change in our neighbourhoods.

    To measure the relationship between changing supply and harm we will link these trajectories, and our measures of availability at each time point, to alcohol and tobacco health outcomes (behaviour, illness and death). We will use statistical models to see whether areas experiencing an increase or decrease in outlets have seen a corresponding increase or decrease in these outcomes. This will allow us to get a better understanding of whether an over supply of alcohol and tobacco is related to smoking and alcohol consumption and harm. These findings will provide important evidence related to the provision of such commodities in our neighbourhoods.

    Although these statistics are important to report we also need to understand why an oversupply of alcohol and tobacco may influence behaviour and harm. Whilst the literature suggests the pathways listed above, we know little about the experiences of individuals living in neighbourhoods with contrasting availability. We don’t understand the individual experience of any of these pathways. Professor Carol Emslie will lead a qualitative work package and researchrs will meet with groups of individuals, in neighbourhoods of contrasting trajectories, to talk to them about the supply of alcohol and tobacco. We will explore their experiences of neighbourhood and assess how their perceived notions of their neighbourhood availability contrast with our statistical measures. Finally, we will meet with residents, retailers and policy stake-holders to explore potential interventions related to supply. Policies at this level require public, retailer and political support. We will discuss the priorities held by various groups, present our quantitative results and gauge attitudes towards potential interventions.

    Throughout the project will be committed to knowledge exchange, public events and speaking with non academic partners. If you wish to know more about this research, or would like one of the researchers to come to your organisation to provide you initial findings (once the project is under way) then contact the Principal Investigator here: niamh.shortt@ed.ac.uk